
Mental Health Billing Software – What to Look For in 2026

TL;DR: What “good” software needs to do now that denial rates and payer requirements have shifted The 8 core processes every behavioral health billing system should support Red flags that mean a current platform has outgrown a clinic, or was never built for it How to evaluate a vendor past the feature list, support, implementation, […]
RCM Denial Management for Behavioral Health – From Reactive to Preventive

TL;DR: Reactive denial management fixes claims after they’ve already been denied. Preventive denial management stops the denial from happening. This piece covers: Why reactive denial management costs more than it looks like it saves What a preventive workflow actually does differently The denial triggers specific to behavioral health claims How to build prevention into the […]
In-House vs. Outsourced Medical Billing – True Cost Comparison for Behavioral Health Facilities
TL;DR: The real cost gap between in-house and outsourced behavioral health billing shows up in denied and complex claims, not routine ones. This piece covers: Why routine claims aren’t where the money is won or lost What denials do to an in-house team’s staffing math What actually changes when billing moves to an outsourced partner […]
California Drug Rehabs Face the Toughest Commercial Billing Scrutiny in a Decade

California drug rehabs face commercial billing scrutiny from four directions in 2026: pre-payment audits, SB 855 parity-driven review tightening, Marketplace authorization narrowing, and state enforcement around patient brokering. Compliant operators need tighter documentation, defensible coding, and audit-ready records to protect revenue.
5 Financial Blind Spots Costing Substance Use Rehabs Thousands

Behavioral health clinics rarely fail because of missing data. They fail because the reports they read are technically correct but operationally misleading. Gross overstates earnings, cash collections lag, a single NCR hides payer-specific bleeding, census outpaces AR aging, and standard buckets miss contract underpayments.
How Manual Billing Quietly Drains Behavioral Health Clinics (And Costs More Than You Realize)

Manual billing in behavioral health looks affordable on the salary line and quietly absorbs cost everywhere else. Lost clinical hours. Dropped admissions calls. Slower cash. Higher denials. Here is what the staffing math actually looks like and where the real cost lives.
In-House Billing vs. CodeMax – What Behavioral Health Facilities Should Know
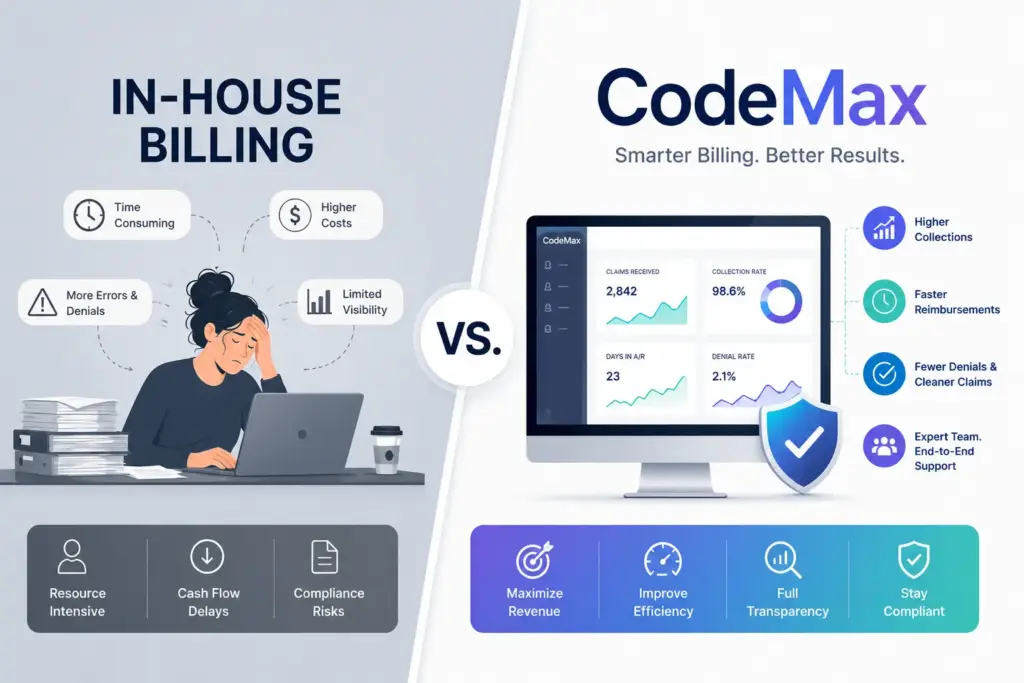
In-house billing teams in behavioral health average AR cycles of fifty to sixty plus days. Outsourced partners average thirty to forty. The performance gap between in-house and specialized behavioral health billing is real and measurable, and it shows up in cash timeline, denial rates, and net collections every month.
How Slow Verification of Benefits Timelines Hurt Florida Rehab Admissions and Revenue
Florida rehab admissions are decision-window events. A patient ready to admit on Tuesday may choose another facility by Thursday if verification of benefits has not cleared. The lost admission never shows up on a denial report. Here is where the verification time actually goes and how parallel workflows compress 48 hours into 6.
What 2026 Reimbursement Changes Mean for Behavioral Health Operators
January 1, 2026 brought the most consequential single-year shift in behavioral health reimbursement since 2016. A Medicare conversion factor split, three new CoCM G-codes, direct Medicare billing for MFTs and MHCs, two new behavioral health telehealth codes, and a 7-day prior authorization decision rule under MHPAEA. Here is what changed, who benefits, and what to do in Q1.
The 7 Places Behavioral Health Revenue Leaks, and How Your Team Misses Them

Behavioral health revenue leakage rarely shows up as one obvious billing failure. It compounds across eligibility, authorizations, undercoding, denials, underpayments, out-of-window services, and self-pay aging. Aggregate dashboards hide each one. Here is where each leak lives, why your team probably misses it, and the three moves that recover the largest share fastest.

